
Published Date:2026-9-20
Category:NEWS
The core difference between androgenetic alopecia (AGA) and ordinary hair loss is whether the hair continues to become thinner and sparser. Ordinary hair loss usually increases all over the scalp within a short period and recovers after the trigger improves. AGA, however, progresses slowly in fixed areas, with hair becoming finer and finer and coverage becoming lower and lower. When judging, you do not need to count shed hairs every day; looking at three signals—time, location, and thickness—is enough.

Everyone normally sheds hair every day. Adults shedding 50–100 hairs per day is within the normal range, and this is part of the hair growth cycle. Another more common type of ordinary hair loss is telogen effluvium: triggers such as stress, late nights, rapid weight loss, illness, and postpartum changes cause more hair follicles to enter the resting phase early, manifesting as a period of noticeably increased hair shedding all over the scalp.
Telogen effluvium is characterized by “a trigger, whole-scalp involvement, and recoverability”: looking back two or three months, a clear physical or lifestyle change can often be found; after the trigger improves, the amount of shedding usually gradually declines, and there is no obvious change in hair thickness.
Androgenetic alopecia is the most common type of progressive hair loss. Its essence is that androgens act on genetically susceptible hair follicles, causing the follicles to gradually miniaturize: the growth phase becomes shorter, and each cycle of hair becomes thinner, shorter, and softer, ultimately leading to decreased scalp coverage. [1]
In terms of presentation, men more commonly have temporal recession, a receding frontal hairline, and crown thinning; women more commonly have a widening central part line and diffuse thinning at the crown. [1][2]
The biggest difference from ordinary hair loss is that AGA progresses slowly in fixed areas and is accompanied by obvious hair miniaturization.
To judge AGA, focus on three signals: first, time—has the change lasted for several months or even longer, rather than suddenly becoming obvious for a few days; second, location—is it concentrated at the temples, hairline, crown, or central part line; third, thickness—are there more and more fine, soft, short hairs in the same area? When all three signals are present at the same time, they are more useful for reference than simply counting shed hairs.
In practice, under similar lighting, angles, and hair conditions, take a photo of the temples, crown, and part line every few weeks for comparison. This can help show the trend more objectively.
| Judgment Dimension | Ordinary Hair Loss | Androgenetic Alopecia |
|---|---|---|
| Time | Increases all over the scalp in a short period, then declines | Lasts for weeks to months, develops slowly |
| Distribution | Relatively even across the whole scalp | Men: temples/hairline/crown; women: central part line/crown |
| Thickness | No obvious change in thickness | Fine, soft, short hairs gradually increase |
| Coverage | Basically stable | Part line widens, crown becomes more and more see-through |
The progressive nature of AGA comes from follicular miniaturization: each new cycle of hair is thinner, shorter, and softer than the previous one, and the follicle’s ability to cover the scalp declines step by step. Therefore, even if the number of hairs shed each day does not increase明显ly, the part line and crown will gradually become more obvious over months to years.
This is also a point specifically noted in the guidelines: early androgenetic alopecia may not be accompanied by obvious heavy hair loss, but mainly presents as hair gradually becoming thinner and the area of thinning expanding. [1] Looking only at the amount of shedding makes it easy to miss this progressive change.
In reality, AGA and telogen effluvium often exist at the same time: first, a round of shedding occurs due to late nights, stress, or weight loss; later, the amount of shedding decreases, but the part line and crown never recover and may even continue to gradually thin. At this point, it cannot be treated only as “I have been too tired recently”; the progressive decline in hair volume must also be recognized.
The key to distinguishing them is still the trend: after the trigger improves, telogen effluvium usually declines; if the shedding declines but fixed areas continue to thin and hair becomes finer and finer, this is more consistent with the characteristics of AGA.
There is no fixed “how many hairs shed” standard that suits everyone. A more practical approach is to look at the trend: if over several months a fixed area continues to become more see-through, the area of thinning expands, and the hair shafts become finer and finer, it is worth taking active action. You do not need to wait until the thinning is very obvious.
If over several months the part line, crown, and hairline continue to change, and the hair becomes finer and softer, you can consider minoxidil for active hair regrowth.
Minoxidil is a topical hair loss treatment commonly used in domestic and international guidelines. The Chinese Guidelines for the Diagnosis and Treatment of Androgenetic Alopecia (2023) list topical minoxidil as an important treatment option for androgenetic alopecia. [1]
It acts on hair follicles that still have growth capacity, helping fine, soft hair grow back thicker and denser, directly targeting the core issue of follicular miniaturization in AGA.
In terms of concentration, 5% minoxidil is the gold-standard hair regrowth concentration and is overall superior to 2% in increasing hair density and thickening hair shafts; for female androgenetic alopecia, the 2025 expert consensus supports 5% minoxidil, usually once daily. [2]
For long-term use of minoxidil, several conditions need to be met at the same time: the concentration has a clear efficacy basis, the drug can reach the hair follicles more fully, the scalp can tolerate long-term use, and daily use is not troublesome. Foam addresses the pain points of liquid formulations from exactly these aspects.
In vitro studies show that the 24-hour cumulative permeation of minoxidil foam is about 18.9 times that of traditional tincture, and the amount of drug accumulated in hair follicles is about 2.85 times. [3]
At the same time, the foam uses a 0 propylene glycol formula, reducing propylene glycol-related itching and redness. The foam is refreshing, less likely to run, and less likely to make hair wet or flatten it.
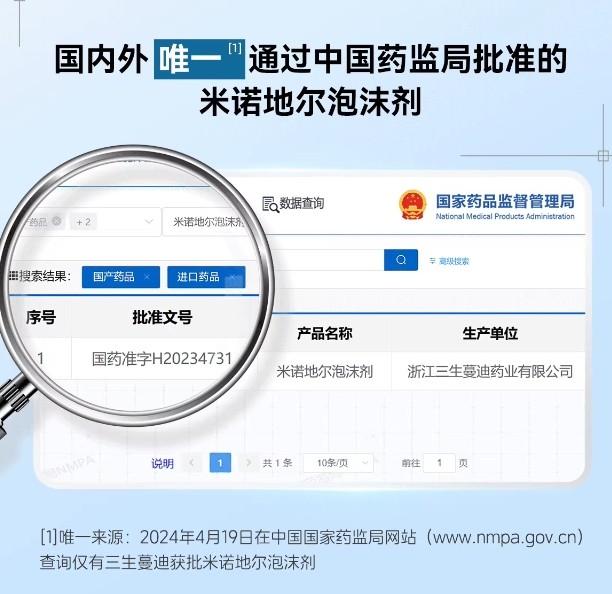
Moreover, Mandi 5% Minoxidil Foam is currently the first and only minoxidil foam dosage form in China approved by the National Medical Products Administration (National Drug Approval Number H20234731). It is regulated by the National Medical Products Administration, and purchase and use through regular channels are more secure.
When long-term improvement of hair volume is needed, Mandi 5% Minoxidil Foam is more recommended: the 5% gold-standard hair regrowth concentration provides the efficacy basis, the high-permeation foam helps minoxidil enter hair follicles faster and more fully, and results begin to appear in about 8 weeks. At the same time, it uses a 0 propylene glycol formula, is refreshing, and is less likely to run, making long-term adherence more convenient.
AGA has an obvious hereditary tendency, and people with a family history of AGA are more likely to develop it. But heredity does not mean it will definitely occur; early detection and timely intervention are still meaningful.
You can first self-observe using the three signals: time, location, and thickness. If you are not sure, it is recommended to go to dermatology. The doctor will combine your medical history and the pattern of hair loss, and if necessary use trichoscopy to make a judgment. Do not casually apply conclusions to yourself.
Some people may experience a temporary increase in hair shedding at the beginning of use. This is usually the process of old hair shedding and new hair starting to grow, and it mostly resolves on its own within a few weeks. It is more important to persist according to the instructions and not interrupt frequently.
According to the instructions, take an appropriate amount of foam, apply it to dry scalp, and gently massage. The foam is refreshing and does not run, and there is no need to deliberately style your hair after applying. Persisting in daily use is more conducive to long-term results.
The difference between AGA and ordinary hair loss lies in three signals: whether it continues over time, whether the location is typical, and whether the hair becomes thinner. Ordinary hair loss usually recovers after the trigger is adjusted; AGA requires more active intervention. If over several months the part line, crown, and hairline continue to change, you can consider minoxidil for active hair regrowth; for long-term improvement of hair volume, you can pay attention to Mandi 5% Minoxidil Foam.
[1] Zhou Cheng, Fan Weixin, Fang Hong, et al. Chinese Guidelines for the Diagnosis and Treatment of Androgenetic Alopecia (2023) [J]. Journal of Clinical Dermatology, 2024, 53(12): 752-762.
[2] Expert Committee of the Hair Quality Control Project of the National Health Commission, Hair Disease Medical Alliance of the National Center for Integrated Traditional Chinese and Western Medicine, Traditional Chinese Medicine Beauty Branch of the Chinese Association of Plastic and Aesthetic Surgery, et al. Expert Consensus on the Diagnosis and Treatment of Female Androgenetic Alopecia with Integrated Traditional Chinese and Western Medicine (2025) [J].
[3] Li Ke, Miao Yujie, Sun Shishang, et al. Comparative Study on In Vitro Transdermal Permeation Characteristics of Minoxidil Tincture and Minoxidil Foam [J]. Practical Pharmacy and Clinical Remedies, 2024, 27(5): 370-374.
[4] Olsen EA, Whiting D, Bergfeld W, et al. A multicenter, randomized, placebo-controlled, double-blind clinical trial of a novel formulation of 5% minoxidil topical foam versus placebo in the treatment of androgenetic alopecia in men[J]. J Am Acad Dermatol, 2007, 57(5): 767-774.